

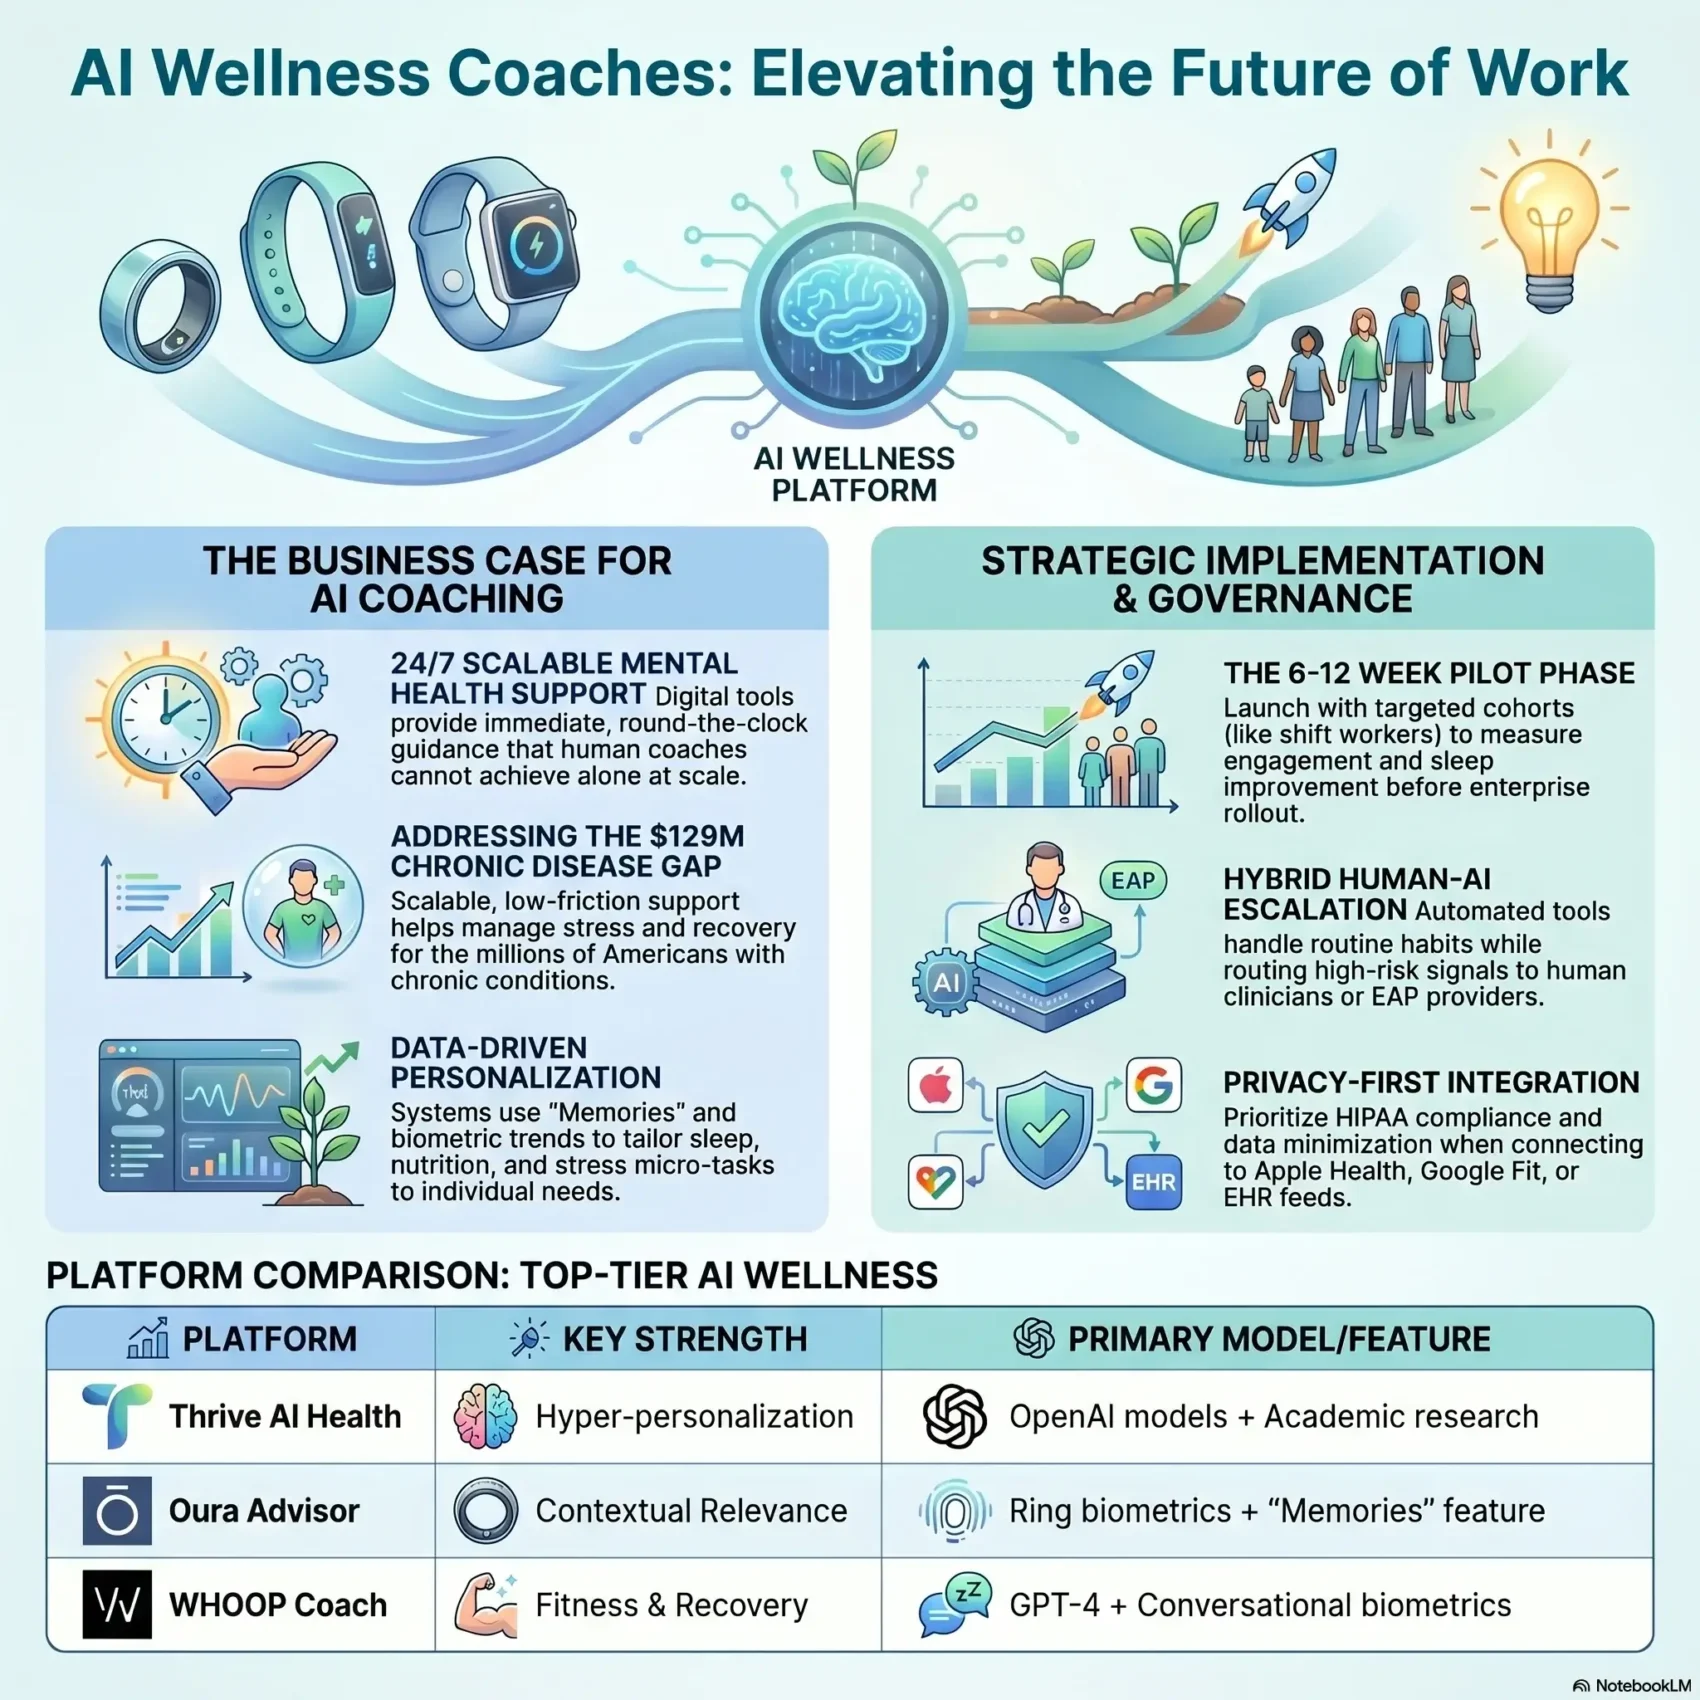
An AI wellness coach is software that reads data from wearables and check-ins, then sends short, personalized suggestions about sleep, stress and activity. It is not a therapist, and it is not a doctor. For employers, it is a way to put some form of support in front of a distributed workforce at any hour, between the moments when a human is available.
This guide is written for the people who have to decide whether that is worth buying: HR, benefits and total rewards leads. It covers what these tools actually do and what the evidence supports in 2026. It also covers what privacy and AI law now require, and how to run a pilot that produces numbers your finance team will accept.
We also cover the parts vendors tend to skip. Consumer wearables are imprecise. Language models still produce confident nonsense. And in the European Union, one entire category of workplace wellbeing AI is now banned outright.
Key Takeaways
- These tools turn wearable and check-in data into small, timed nudges. They work best as a layer on top of human support, not as a replacement for it.
- Global engagement sits at 20% and only 34% of employees are thriving, so the demand for cheaper, always-available support is real (Gallup, 2026).
- Since 2 February 2025 the EU AI Act bans AI that infers employee emotions from biometric data at work, with only narrow medical and safety exceptions.
- Consumer wearables are good at trends and weak at absolute accuracy, so never let a device reading drive a clinical decision.
- Budget for integration, security review and communications, not just the per-user licence. Those line items decide whether the rollout lands.
What an AI wellness coach actually is
Picture an employee who slept badly for four nights running. Their ring or watch has recorded it. At 2pm, when their focus usually collapses, the app sends one line: a suggested ten-minute walk and a reminder to stop caffeine after 3pm. That is the whole product in one sentence.
Technically, it is a conversational layer on top of a data pipeline. The system reads biometric feeds and self-reported check-ins, then looks for patterns. A language model turns those patterns into plain advice you can act on in a few minutes.
How it differs from a human coach
A human coach brings judgment, empathy and the ability to notice what someone is not saying. Software brings availability and scale. It answers at 3am, it never forgets to follow up, and it costs roughly the same whether 50 or 5,000 people use it.
The strongest programs use both. The software handles tracking, reminders and routine guidance. Humans handle the complicated cases, the resistance, and anything that looks clinical. If your vendor positions the tool as a substitute for people, treat that as a warning sign rather than a feature.
Most tools cover a similar core: sleep habits, stress coping skills, gentle movement, and basic nutrition prompts. That is deliberate. These are low-risk topics where general advice rarely harms anyone.
Why employers are looking at this in 2026
The demand side is easy to explain. Gallup’s State of the Global Workplace 2026 put global employee engagement at 20% in 2025, its lowest level since 2020, with 34% of employees thriving in their overall lives. Those numbers have not moved in the direction employers hoped, and traditional support keeps running into the same two walls: cost and access.
Access is the sharper problem in the United States. The CDC’s National Center for Health Statistics reported that 8.3% of Americans, or 28.0 million people, had no health insurance in 2025. Your workforce is spread across time zones and coverage situations. Something that works on a phone at no marginal cost per session is useful there, even if it is limited.
Chronic conditions add weight to the business case. The American Action Forum, citing 2023 CDC data, reports that 129 million Americans live with at least one major chronic condition. Sleep, movement and stress habits sit upstream of many of those conditions, which is why employers keep returning to prevention.
Where this fits in your existing stack
Think of it as the widest, thinnest layer in your virtual employee wellness program. Below it sit your EAP, behavioral health vendors and clinicians, who handle fewer people at much greater depth.
It solves a different problem than wellbeing stipends, which give employees money and let them choose. A coaching tool gives structure instead of budget. Many employers run both, and the pairing works as long as you are clear which problem each one addresses. If your main issue is workload rather than habits, read our piece on employee burnout and the future of work first, because no app fixes an unrealistic staffing plan.
How the technology works
Understanding the pipeline helps you ask better questions in a vendor demo. There are three stages: collect, interpret, deliver.
Data sources
The common feeds are Apple Health, Google Fit, Oura, WHOOP, plus in-app check-ins where users log mood, energy or meals. Sleep duration, activity and heart rate variability (a measure of the small timing differences between heartbeats, often used as a rough recovery signal) produce most of the useful suggestions.
Some vendors also connect to clinical records. WHOOP announced a partnership with HealthEx in May 2026 that syncs electronic health records, including diagnoses and medications, into the member’s profile. That adds context and a great deal of governance work, so treat it as an advanced option rather than a starting point. Our guide to wearable technology in workplaces covers the device side in more detail.
From raw numbers to advice
Machine learning finds the patterns. Natural language processing, meaning the part of the system that reads and writes human sentences, turns those patterns into a message and answers follow-up questions.
The quality of what comes out depends almost entirely on what goes in. A tool with three weeks of sleep data and no check-ins will give generic advice, because that is all the data supports.
Personalization levers
Personalization comes from three places: stated goals, observed behavior, and stored context. Oura’s Advisor keeps “Memories” so it can remember that someone travels every second week. WHOOP added a similar feature called My Memory in May 2026, alongside proactive check-ins that fire before a big event or after long travel.
Tone settings matter more than they sound. The same advice reads as supportive or nagging depending on phrasing, and phrasing is the main reason people stop opening an app.
What employers can realistically expect
Be careful with the benefit claims here. Independent evidence on workplace wellbeing apps is thin, and vendor case studies are marketing. What follows is what the mechanism plausibly delivers, stated honestly.
Support that arrives between appointments
The clearest benefit is timing. A prompt that arrives at the moment someone is deciding whether to go to bed is worth more than the same advice in a quarterly newsletter. This is the same logic behind the habit work in our guide to sleep and productivity.
Reach without proportional cost
A human coaching program that reaches 200 people costs roughly ten times one that reaches 20. Software does not work that way. That lets you keep human capacity for the cases that need it, which is a real budget argument even if the health outcomes stay modest.
Population-level signal
Aggregated, anonymized dashboards can show that one business unit reports far more stress than the rest. That is useful input for benefits design and for the conversations covered in our look at remote employee engagement.
One caution. The moment employees suspect that wellbeing data feeds into management decisions, participation collapses. Keep reporting aggregated, say so in writing, and mean it. The trust dynamics are the same ones described in our article on AI in employee monitoring.
The main platforms to know in 2026
Pricing for enterprise deployments is almost always quoted rather than published, so treat the list below as a starting point for demos, not a price comparison.
Thrive AI Health
Launched in July 2024 by the OpenAI Startup Fund and Arianna Huffington’s Thrive Global, this venture pairs OpenAI models with Thrive’s Microsteps method and academic partners. The pitch is hyper-personalized behavior change built on very small actions.
Oura Advisor
Built on ring biometrics, with selectable interaction styles and stored Memories. Strong on sleep and readiness, and comfortable for people who dislike wrist devices.
WHOOP Coach
Conversational guidance built around strain, recovery and sleep. WHOOP announced on-demand video consultations with licensed clinicians for US members in summer 2026, which moves it closer to a care pathway than most consumer tools.
Humanity and ONVY
Humanity gamifies longevity with daily scores and biological age estimates. ONVY pairs recovery and sleep scores with specific daily targets. Both suit employee groups who respond to numbers and streaks.
Lark Health and Noom
Both run structured behavior-change programs rather than open-ended chat, with a stronger focus on nutrition and chronic condition management. They pair well with device-led tools.
When you compare them, judge four things: personalization depth, content quality, response speed, and how the vendor handles escalation. Our AI assistants overview is a useful companion when you write the vendor questionnaire.
Feature checklist for your shortlist
Use this to compare vendors side by side and to spot gaps before a pilot rather than after it.
- Core coverage: sleep, stress skills, movement and basic nutrition, expressed as tasks someone can finish today.
- Evidence: visible sources behind recommendations, with a stated update cycle. Stale content is a liability.
- Personalization: does it use biometric context and stored history, or is it a generic chatbot with your logo on it?
- Escalation: written thresholds, scripts and response times for routing someone to a clinician or your EAP.
- Accessibility: screen reader support, plain language, and consistent behavior across phone and desktop.
- Administration: cohort dashboards and exportable reports that your benefits team can actually read.
- Integrations: Apple Health and Google Fit at minimum, HRIS for provisioning, clinical feeds only if you truly need them.
The same discipline applies here as in any employee experience platform purchase: shortlist on the requirements you can verify, then test the rest in a live pilot.
Privacy, HIPAA and the EU AI Act
This is the section that most often kills a deal late, so handle it early.
What HIPAA does and does not cover
Data an employee generates on a consumer wearable is usually not protected health information, because the device maker is not a covered entity. That surprises people. If your program routes data through a health plan or a clinical provider, HIPAA can apply and your vendor may become a Business Associate. Get a written answer on which category each data flow falls into, and store that answer with your workplace data privacy documentation.
Collect the minimum that makes the guidance useful. Define retention, deletion and consent before launch, and publish a short, readable explanation of what you collect and why. A wearable tech policy is the natural place for those rules.
The EU line you cannot cross
Since 2 February 2025, Article 5(1)(f) of the EU AI Act prohibits AI systems that infer the emotions of a person from biometric data in the workplace. The exceptions are narrow: therapeutic or CE-marked medical uses, and safety reasons limited to protecting life and health. Guidance from the European Commission says these exceptions must be read strictly.
In practice, a tool that suggests a breathing exercise because you slept badly is not the problem. A tool that scores an employee’s emotional state from their voice or face is. If a vendor demonstrates anything resembling mood detection from biometrics for EU staff, stop the demo. Our article on emotion recognition AI at work goes through the boundary in detail.
A second date matters. From 2 August 2026, the AI Act’s Article 50 transparency rules require that people are told when they are interacting with an AI system, unless it is obvious. Your onboarding copy and the chat interface itself should make that clear. Fold both requirements into your AI governance policy rather than treating them as a one-off task.
Bias and wrong answers
Ask how the vendor audits for bias, how recommendations are grounded in sources, and what happens when the model produces something unsafe. Require evidence, not assurance. Language models still fabricate, and health advice is a bad place to discover that.
Limits and when not to use it
Set the boundary in writing before launch, because ambiguity here creates real risk.
Automated coaching suits low-risk, everyday guidance: habit prompts, sleep hygiene, movement reminders, general stress skills. It does not suit anything that looks clinical. Suppose an employee reports persistent low mood, a significant change in behavior, or any sign of crisis. The system’s job then is to route them to a human quickly and clearly, not to keep coaching.
Two technical limits deserve a plain warning to users. Wrist-worn heart rate sensors lose accuracy during intense exercise, and consumer sleep staging is imprecise. These devices are useful for spotting trends over weeks. They are not diagnostic instruments, and your communications should say so in the first week rather than the first complaint.
There is also an empathy gap. Software can be written to sound caring. It cannot notice that someone has gone quiet in a way their manager would. Keep managers trained and involved, and keep at least one human touchpoint in the program. Our guide to remote work and mental health covers what that looks like in a distributed team.
Finally, watch for the tool that quietly extends the workday. If nudges arrive at 10pm and employees feel they should respond, you have added pressure rather than removed it. Align the notification schedule with the boundaries in your right to disconnect approach.
Pricing, ROI and total cost
Vendors use per-user subscriptions, tiered bundles, or enterprise licences with add-ons for analytics and clinical connectors. Per-user pricing is simple to budget and gets expensive fast at full enrollment. Tiered models let you start with core coaching and add analytics later, which usually suits a first year better.
The costs that are not on the quote
Expect integration engineering, legal and security review, employee communications, manager enablement and ongoing admin time. On a first deployment, these routinely cost more than the licence itself. Build them into the business case rather than discovering them in month two.
Measuring impact honestly
Pick metrics you can defend: active users over time, self-reported sleep and stress measures, EAP referral volume, and absence data. Claims trends move slowly and have many causes, so quote them directionally or not at all.
When a vendor presents savings, ask three questions. What was the comparison group? How did you control for people who were already motivated? What is the confidence interval? A vendor that cannot answer those is showing you marketing, not evidence. The wider benefits context in our overview of the evolution of employee benefits is useful when you frame the request to finance.
Implementation playbook
Run a narrow pilot first. It protects your credibility and it produces the numbers you will need for a wider rollout.
Pilot design
Pick one cohort with a clear, shared pressure: a shift team, a support function in peak season, or a group with heavy travel. Run it for six to twelve weeks. Agree the success measures before launch, and include a comparable group that does not get the tool if you can.
Put a data-sharing agreement in place that limits scope, retention and export rights. Start with Apple Health and Google Fit only, and leave clinical integrations for later. Enrollment should be opt-in, with an obvious way out.
Change management
Give managers a short briefing and a one-page FAQ. The two questions employees always ask are whether their employer can see their data and whether participation affects their review. Answer both in writing, in the first communication, in plain language.
Open a feedback channel and actually read it. Most early complaints are about notification timing and tone, and both are usually fixable in settings.
Governance
Document escalation rules, response times and vendor service levels. Schedule a quality review after the pilot that looks at a sample of real conversations, not just the dashboard. Set a content update cadence and a date to revisit the AI Act obligations, which continue to phase in.
Two pieces make useful background reading for the steering group: our summary of current HR trends and our guide to stress management at work.
Conclusion
An AI wellness coach is a reasonable addition to a wellbeing program and a poor substitute for one. It extends reach at low marginal cost, it arrives at moments a human cannot, and it produces aggregate signal you would otherwise never see.
It also inherits every weakness of the data underneath it and every limitation of the models on top. Wearables are imprecise. Models make things up. Neither of those facts disqualifies the category, but both belong in your risk register and in your employee communications.
Start small, define the escalation path before the first user logs in, and insist on evidence rather than testimonials. If the pilot shows engagement and no harm, scale it. If it does not, you will have spent one quarter and a modest budget to learn something useful. Our AI assistants overview is a good next stop when you write the vendor questionnaire.
Found this useful?
Make SmartKeys a preferred source on Google, and our articles will surface more often in your Top Stories, AI Overviews, and AI Mode.
Add as Preferred Source




